
The Gut Skin Connection: What Your Breakouts Are Telling You About Your Digestion
The gut skin connection plays a major role in acne, inflammation, hormone balance, digestion, and overall skin health. You have done the things for your skin. That is what makes this so exhausting.
You have been to the dermatologist, probably more than once. You have taken the antibiotics, and maybe the spironolactone, and maybe the Accutane, and you remember exactly how your skin looked during and exactly how it looked six months after. You have a drawer of half-used products that each worked beautifully for about three weeks. You have cut out dairy. Then gluten. Then sugar, then nightshades, then whatever the last person told you was the real culprit. You have looked at your own face in a bathroom mirror at eleven at night, trying to decide whether today was better or worse than yesterday, and you have canceled things, or almost canceled things, because of how it looked.
Somewhere in all of that, you probably started to suspect that the problem is not actually on your face.
You are right. And I want to say something before we go any further, because I think you have been carrying it for a while.
This is not your fault. You did not cause this by eating the wrong thing, by not being disciplined enough, or by stressing too much about it, and the amount of effort you have put into fixing it is genuinely the reason you are still functioning as well as you are. Your body has responded exactly as it would to the inputs it was given. Nothing about you is broken, and nothing about your case is uniquely difficult.
The other thing worth saying is that your instinct was correct. You suspected something systemic was going on, and you were probably told, possibly by more than one professional, that it was unrelated, or normal, or just how your skin is. Being dismissed like that enough times will make anyone stop trusting their own read on their body. Your read was right.
And every protocol that stopped working after three weeks was not evidence about you. It was the wrong target, or the right target in the wrong order, applied to a system that had never been prepared for it. That distinction matters more than it sounds, and I will come back to it. And I want to tell you about someone whose story might sound familiar, because what finally explained her skin is something almost nobody had thought to look for.
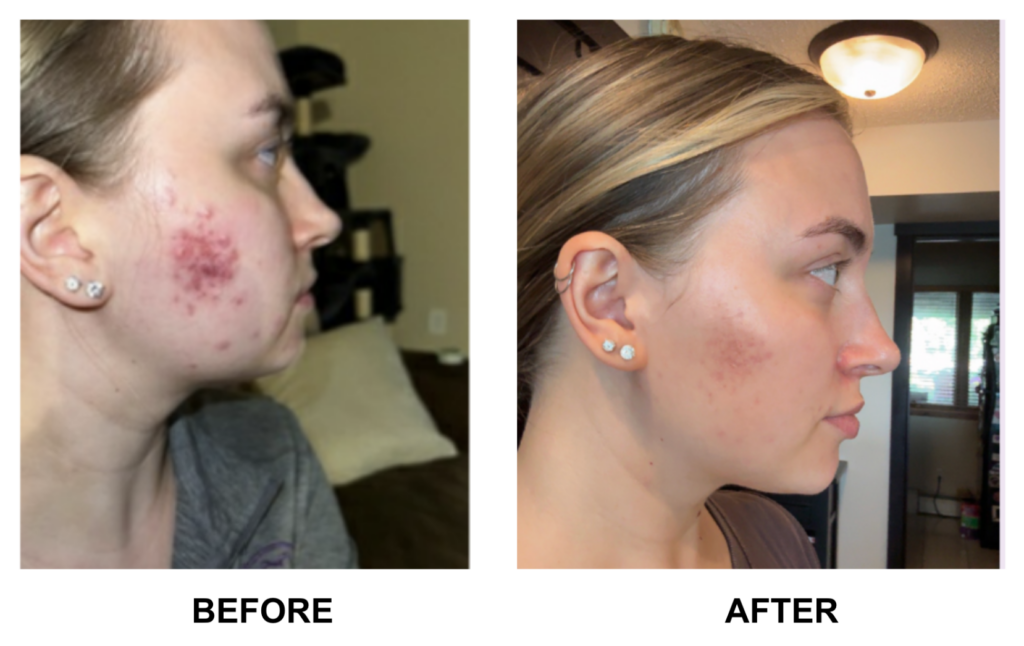
She was twenty-five and had been dealing with acne for eight years. Every prescription, every topical, every elimination diet, every product a dermatologist or an aesthetician or the internet had suggested. Some of it worked for a few weeks. None of it held.
The thing that finally explained it was that it had happened a decade earlier, and nobody had ever connected the two. Between the ages of sixteen and twenty, she had gone through ten to fifteen courses of antibiotics for a recurring MRSA infection. At the time, it was the right call. What nobody warned her about was what it would leave behind.
By the time she came to me, her testing showed significant dysbiosis, bacterial overgrowth in her small intestine, and a zonulin level well above range, which is the clearest marker we have for a compromised intestinal barrier. That barrier was allowing bacterial endotoxins into her bloodstream; her immune system was responding to them systemically rather than locally, and her skin was where it all surfaced. Then, the way these things tend to, it began feeding itself. The acne made her anxious, the anxiety raised her cortisol, and the cortisol made the acne worse.
For eight years, everyone had been treating her face. Her skin cleared over the following six months, and not because we found a stronger prescription. It cleared because somebody finally went looking upstream.
Watch her full case overview here, where I walk through the actual testing, what it showed, and the order we worked in.
If any of that landed, keep reading, because I want to walk you through what upstream actually means. Once you understand it, a lot of what has felt random about your own skin starts to make sense.
Your Skin Is Not a Surface Organ. It Is a System Organ.
Everything else in this article depends on this one reframe, so let me be as clear as I can about it.
Your skin is not a covering. It is an output. What you see in the mirror on any given morning is a live readout of your gut integrity, your microbial balance, your hormonal signaling, your detox capacity, how activated your immune system is, and what tone your nervous system is holding. Those six things determine whether your skin is calm or reactive, and no topical, however well-formulated, changes any of them.
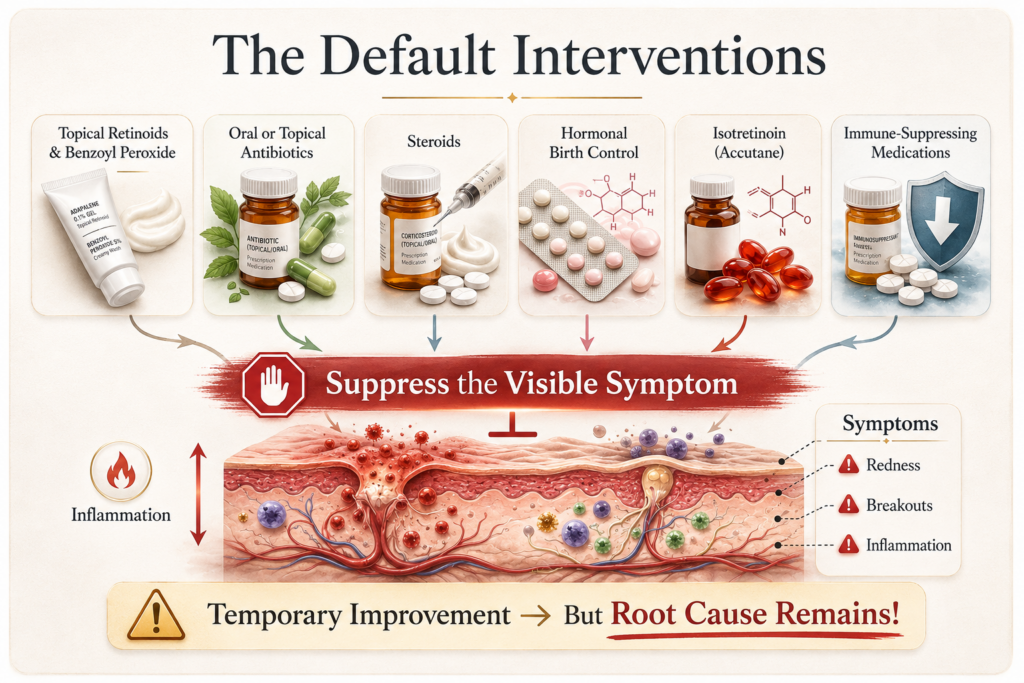
None of which means conventional dermatology is wrong. It is genuinely very good at what it does: suppressing what has already shown up. Antibiotics reduce bacterial load. Retinoids normalize turnover. Steroids calm inflammation. Hormonal suppression lowers androgen signaling. These are real tools, and there are absolutely situations where they are the right call, including some where they are the only reasonable call.
The question they do not answer is why. Why is your inflammation elevated in the first place? Why are your hormones imbalanced? Why is your gut barrier compromised, why are your detox pathways overwhelmed, why has your immune system become reactive, why is your skin barrier so fragile that products you used to love now sting. Leave those unanswered, and the condition comes back the moment you stop suppressing it, which is not a failure of discipline on your part. It is simply what happens when you treat an output as though it were the cause.
It helps to think about what your skin is actually doing all day. It replaces itself completely about every twenty-eight days, and every single one of those cycles demands protein, zinc, vitamin A, vitamin C, essential fatty acids, and a long list of cofactors behind them. It is one of the most metabolically expensive tissues you own. It is also, as far as your body is concerned, entirely optional.
Your body will fund your heart and your brain and your immune system long before it funds your face, so when resources run short, or inflammation runs high, or absorption is impaired, your skin is among the first places you will see it. That makes skin a wonderful early warning system and a fairly useless place to intervene on its own.
It also explains something most people have noticed but been told to ignore: skin symptoms almost never appear on their own. There is usually fatigue somewhere in the picture, or bloating, or brain fog, or a cycle that has quietly gotten worse over a few years, or sleep that stopped being restorative at some point you cannot quite pinpoint. Most people have been handed a different specialist for each of those and told they are unrelated. In my experience, they are usually the same picture surfacing in whichever tissue happens to be least protected at the time.
This is also why the diagnosis you were given tells you less than you would hope. Hormonal acne is really an endocrine and metabolic story. Fungal acne is microbiome instability. Bacterial acne is an ecosystem that has lost its balance. Dermatitis is barrier failure layered with immune overactivation, rosacea is immune and vascular dysregulation, and psoriasis is autoimmune inflammation. Six different labels, all of them drawn from the same small set of upstream systems in different combinations and different proportions. Which is why two people can walk in with acne that looks identical and need completely different interventions, and why the protocol that transformed your friend’s skin did absolutely nothing for yours.
How Your Gut Actually Reaches Your Face
The gut and the skin talk to each other constantly, through the immune system, through hormonal signaling, through inflammatory mediators, and through the metabolites your bacteria produce. There are four mechanisms doing most of that work, and they are worth understanding individually because they call for different solutions.
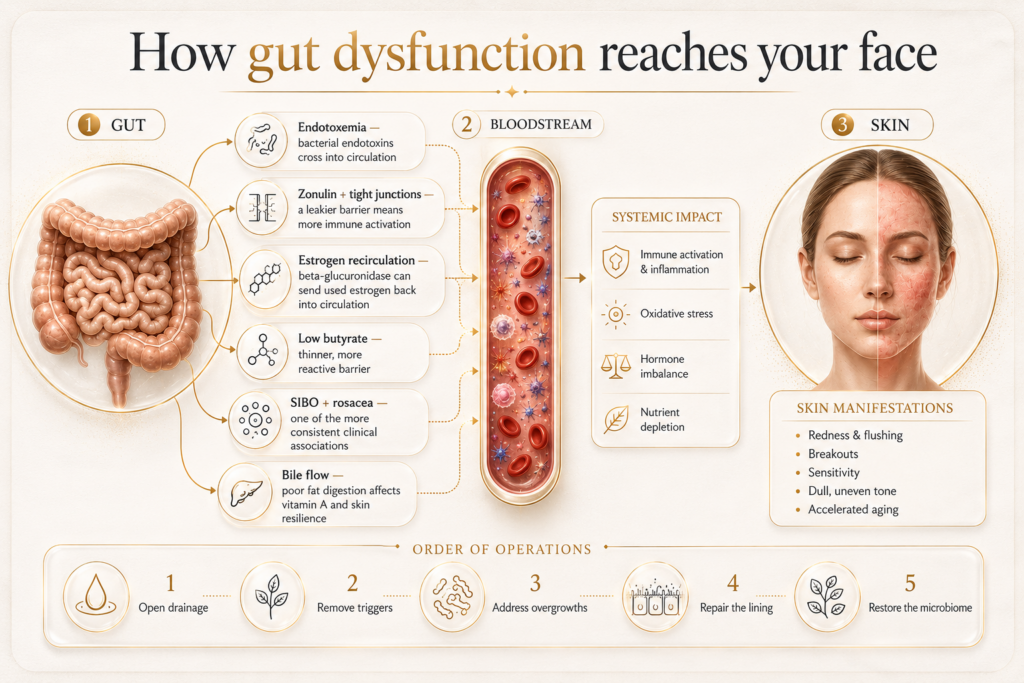
Endotoxins Crossing Into Circulation
Your intestinal lining is a single cell thick in places, held together by protein structures called tight junctions, which is a remarkable piece of engineering when you consider what it is separating. When that barrier loosens, fragments of bacteria called endotoxins slip into your bloodstream, and your immune system responds to them the way it responds to any perceived threat, which is systemically rather than locally. The result is low-grade inflammation more or less everywhere, and skin is one of the most common places it becomes visible. This is why inflammatory skin conditions so often accompany fatigue, brain fog, and aching joints, and why treating them as separate problems tends to get nowhere. They are one problem wearing several costumes.
Zonulin and a Leaky Barrier
Zonulin is the primary regulator of those tight junctions, and when it is elevated, the barrier becomes more permeable, leading to increased immune activation and a greater inflammatory load carried around all day.
There is a practical consequence here that I wish more people knew about, because it can save a lot of unnecessary suffering. If the list of foods you react to keeps getting longer, that is almost never a food problem. It is a barrier problem. Cutting out one more food treats the symptom while the actual cause carries on unchanged, which is how thoughtful, disciplined people end up eating twelve safe foods and wondering why their skin has not budged.
So if you are currently looking at your food list wondering what else to remove, I would like to gently take that option off the table. More restriction is not the next move. The goal here is to get foods back, not to find another one to lose. A shrinking diet is a sign that the barrier needs attention, and it is also its own kind of stress on a body that is already carrying plenty.
Estrogen Going Back Into Circulation
Your gut is a hormonal organ, which is the part that surprises people most. Your liver does the work of packaging used estrogen for excretion, but certain gut bacteria produce an enzyme called beta-glucuronidase that unpackages it again and sends it back into circulation instead of out of your body.
So a picture that looks unmistakably hormonal on your face can turn out to be a microbiome problem rather than a production problem, which is a large part of why hormone panels on their own so often fail to explain what someone is seeing in the mirror.
The Short Chain Fatty Acids That Keep Everything Calm
When you eat fiber, certain bacteria ferment it into short-chain fatty acids, and one of them, butyrate, does an enormous amount of quiet work. It feeds the cells lining your gut and helps regulate immune activity. Low microbial diversity means less butyrate, which in turn means a thinner, more reactive gut barrier and an immune system running on a shorter fuse. If your skin flushes easily, stings, and has started reacting to products it tolerated fine a year ago, this is very often what is underneath it.
How You Probably Got Here
The story I told at the start involved antibiotics, but that is only one of the roads into this, and it is not the most common one. Most people arrive here by a different route, and it is worth finding yours, because what a treatment leaves behind shapes what you need to do now.
- You were put on birth control for your skin. This is the most common path by a wide margin. You were fifteen or sixteen, your skin was bad, and someone offered you something that worked. And it did work because suppressing ovulation lowers androgen activity, which in turn lowers sebum production. What it did not do was address why your androgens were driving your skin in the first place, so that question simply went unasked for the next decade while the underlying picture carried on quietly.
There is a second layer: hormonal contraceptives are associated with depletion of several nutrients your skin depends on, including B6, B12, folate, zinc, magnesium, and selenium, and they alter the gut microbiome. So a fifteen-year-old with an unexamined androgen and blood sugar picture becomes a twenty-eight-year-old with an unexamined androgen and blood sugar picture, less nutrient reserve, and a different microbiome than she started with.
Then she comes off, and her skin does something dramatic. That is not simply her old acne returning. It is androgen rebound, which typically builds over the first three to six months and can take a year or more to settle, arriving on top of everything that was never addressed underneath. It settles faster when the drivers get support rather than being left to sort themselves out.
- You did a round of Accutane. Or two, because relapse is common enough that second rounds are routine. Isotretinoin is a genuinely powerful drug and for some people it is curative, and I am not going to pretend otherwise. It also does substantial things beyond shrinking sebaceous glands. It thins the skin barrier, it is demanding on the liver, it dries mucous membranes throughout the body rather than only on your face, and it affects the absorption and status of fat-soluble vitamins. If your skin has been fragile, reactive, and dry ever since, or if your digestion changed around that period and never quite went back, that is worth taking seriously rather than treating as coincidence.
- You have been on prescription topicals for years. Clindamycin, benzoyl peroxide, a retinoid, often several at once and often for a very long time. Topical antibiotics disrupt the skin microbiome the same way oral ones disrupt the gut, and the retinoid your barrier tolerated at twenty may be more than it can handle at thirty-two. If your skin has become progressively more reactive over the years rather than less, this is frequently why.
- You were given steroids. For eczema, for dermatitis, for a flare somebody wanted to shut down quickly. They work, and then there is rebound when you stop, and the rebound gets treated with more steroid. Perioral dermatitis in particular has a cruel habit of worsening under exactly the treatment prescribed for it.
- Or you did everything right and cut foods for years. Dairy, gluten, sugar, nightshades, whatever the last article said. Long elimination narrows plant diversity, which in turn narrows bacterial diversity, reducing the butyrate that keeps your gut lining fed and your immune system regulated. The diet that was supposed to calm your skin can quietly work against the system underneath it.
I want to be clear that none of these were wrong to take. Every one of them is a reasonable tool, and most were prescribed in good faith by people trying to help you. The problem is not that you took them. The problem is that nobody looked at what they left behind, or at what was driving the situation that made them necessary in the first place. That is the part still waiting to be done, and it is doable.
What This Looks Like in Real Life
The mechanisms are useful, but most people recognize themselves in the patterns rather than in the biochemistry, so here are the ones I see most often.
Your skin got worse after antibiotics, or it got better first and then noticeably worse. Antibiotics reduce microbial diversity and the recovery is frequently incomplete, and what tends to follow is fungal overgrowth, because the bacteria that had been keeping yeast in check are gone. That matters more than it sounds, because fungal acne is not actually acne at all. It is Malassezia folliculitis, an overgrowth of yeast inside the hair follicle, and treating it like bacterial acne usually makes it worse rather than better. If your bumps turned small, uniform, and itchy across your forehead, chest, or back after a course of antibiotics, a round of steroids, or a humid stretch of weather, there is a real chance you have been treating the wrong thing for a long time.
Or you bloat and break out in the same week, which people tend to mention almost apologetically, as though it were a coincidence they are embarrassed to have noticed. It is not a coincidence. Both are pointing upstream at the same picture.
Or you have rosacea alongside digestive symptoms. Rosacea is not acne, no matter what it looks like. It is a neurovascular and immune condition involving mast cell activation, an overactive innate immune response, gut dysbiosis with a well-documented link to small intestinal bacterial overgrowth, increased intestinal permeability, and a nervous system that has become hyper-reactive. If you flush easily and also deal with bloating or unpredictable stools, that connection deserves investigating rather than another year of managing the redness from the outside.
Or red bumps appeared around your mouth and nose after a period of heavy product use. Perioral dermatitis stems from barrier damage caused by overusing actives, steroid rebound, microbiome disruption, hormonal shifts, and, frequently, gut dysbiosis beneath it all. It has the particularly cruel habit of getting worse with the steroids commonly prescribed to treat it.
And then there is the version that confuses people most: when digestion feels completely fine, but the skin does not. I want to say this one plainly, because it stops a lot of people from investigating: you can have meaningful gut dysfunction without a single obvious digestive symptom. Absorption, barrier integrity, and microbial balance can all be substantially off in someone who never bloats and never thinks twice about their stomach. Sometimes your skin is the only signal you get.
Not Sure Which System Is Driving Yours?
I built a free assessment that walks you from what you see in the mirror down to what is likely causing it. Ten questions, about four minutes. It scores your answers across eight root cause domains and shows you which ones your symptoms point to most strongly, along with what to do about each.
Take our Root Cause Skin Assessment
Why Normal Labs Do Not Rule Any of This Out
One of the most common things I hear is that someone’s bloodwork came back fine, so hormones were ruled out and everyone moved on.
I worked with a client whose acne was severe and adult-onset, running along her jawline, cheeks, neck, chest, and back. She also had thinning hair at her scalp and increased facial hair. Clinically, that is an androgen pattern in every direction you look at it. Her labs came back showing low androgens.
That is not the contradiction it appears to be. Bloodwork measures the hormones circulating in your blood. It does not measure how sensitive the receptors in your skin are, nor how much hormone is converted and activated locally within the tissue itself by an enzyme called 5-alpha reductase. You can have unremarkable circulating levels and a follicle that is responding as though levels were high.
Her gut testing, meanwhile, showed high levels of opportunistic bacteria, low levels of beneficial species, low secretory IgA, and clear evidence of intestinal inflammation, and her inflammatory fatty acid ratio was several times the upper limit of the reference range. Her estrogen was high. Taken together with the jawline distribution, the hair changes, and the digestive symptoms she had stopped mentioning to anyone, it is a completely coherent case. Taken one number at a time, every finding looked ordinary enough to dismiss, which is exactly what had been happening for years.
So Which One Is Yours
I cannot tell you that from here with certainty, and anyone who says they can from a photograph is selling something. But these patterns are recognizable, and most people find themselves fairly quickly in one or two of them.
If it sits along your jawline, chin, and neck, and it is deep, cystic, and worse the week before your period, you are most likely looking at an androgen and blood sugar picture. Look for the other signals that travel with it: thinning at your scalp or crown, increased facial or body hair, afternoon energy crashes with sugar cravings, weight that will not move around your middle. The first move is not a topical. It is stabilizing blood sugar, which means having protein at every meal, eating carbohydrates with fat and fiber rather than alone, and no grazing between meals. That alone shifts a surprising number of these cases.
If the bumps are small, uniform, itchy, and clustered on your forehead, chest, back, or shoulders, and they appeared after antibiotics, steroids, heat, or heavy sweating, this may well be fungal rather than acne, and acne treatments are probably making it worse. The first move is to stop feeding it: switch to skincare without the fatty acid esters that Malassezia thrives on, which means avoiding palmitates, stearates, and oleates on the ingredient list, and reduce the sugar load in your diet while you sort out the rest.
If it is persistent redness, flushing, visible capillaries, and skin that burns or stings, particularly with heat, alcohol, spice, or exercise, that is an immune and vascular picture rather than an acne one. The first move is to identify your specific flush triggers and reduce the histamine load while you address the underlying gut piece, because rosacea and small intestinal bacterial overgrowth often travel together enough that it is worth ruling them in or out.
If this started or intensified within a year of coming off hormonal birth control, you are likely dealing with androgen rebound layered on top of whatever was never addressed before you went on it, often with nutrient depletion underneath. The first move is the same as the androgen pattern above, plus rebuilding the nutrients the pill depletes, and some patience, because this one has its own timeline regardless of how well you handle it.
If your skin has become reactive to products it used to tolerate, stings on application, and feels tight after washing, your barrier is compromised, and no active is going to work on top of it. The first move is subtraction, which I will come to in a moment.
If your skin tracks your stress with a two- or three-day delay, and you are wired at night and exhausted in the morning, this is nervous-system-driven and will not respond to a gut protocol alone. The first move is regulation: consistent sleep timing, morning light before screens, and slowing your breathing before you eat rather than after.
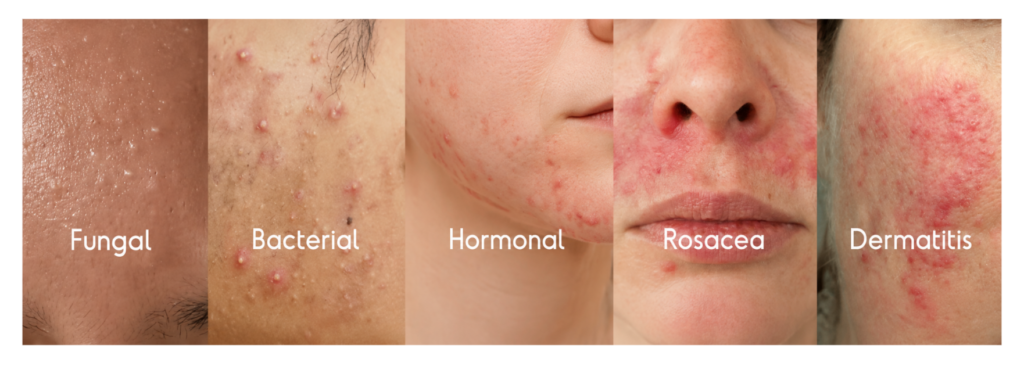
Most people are some combination of these, which is exactly the problem with treating any one of them in isolation. If you want the ranked version specific to your own symptoms, that is what the assessment does.
Your Barrier Is Not Cosmetic
While all of that is going on internally, there is a second conversation happening on the surface, and it deserves more respect than the skincare industry generally gives it.
Your skin barrier is a biological system. It works as an immune organ, as a living microbial ecosystem, as a water regulation system, and as your first line of defense against anything trying to get in. It is home to trillions of bacteria, fungi, mites, and viruses that protect you, keep each other in balance, and communicate constantly with your immune system.
I damaged mine badly, so this is not theoretical for me. I over-exfoliated, over-treated, and under-repaired for years. I was trying to force clarity instead of restoring structure, and the harder I pushed, the more reactive my skin became.
What damages a barrier is fairly predictable once you know to look for it: over-exfoliating with acids and scrubs, using retinoids more aggressively than your skin can tolerate, harsh surfactants like SLS, alcohol-heavy toners, chronic topical steroids, repeated antibiotics, fragrance and essential oils, and cleansers that foam enthusiastically and leave your face feeling squeaky. Almost all of that comes from doing more rather than doing less, which is worth sitting with if your routine has grown steadily over the past few years. More product does not produce better skin.
What supports a barrier is much less exciting to buy. Formulations balanced to your skin’s actual pH, minimal surfactants, oils chosen to match your specific condition rather than whatever is trending, hydration that does not suffocate, avoiding the fatty acid esters that feed yeast if Malassezia is part of your picture, and no fragrance that is not doing a job. The principle underneath all of it is that skincare should support your ecosystem rather than sterilize it.
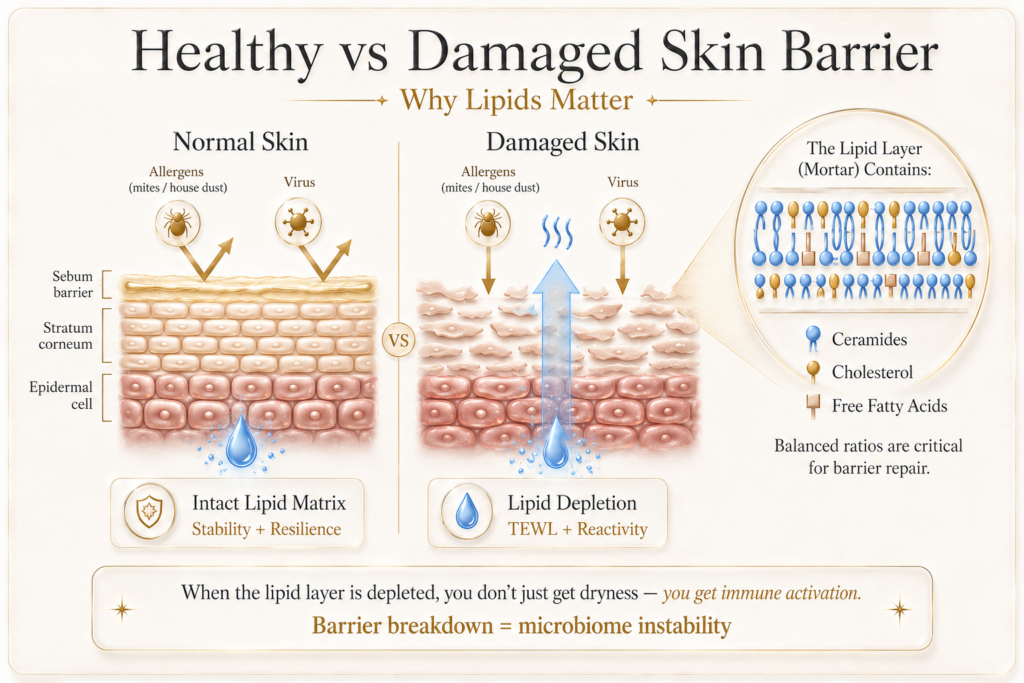
Once the barrier is genuinely holding, the actives earn their place, and they are worth using. Daily broad-spectrum sunscreen, because UV degrades collagen and drives pigmentation faster than anything else you encounter. Retinoids for collagen and turnover. Vitamin C with E and ferulic acid for oxidative protection and tone. Niacinamide, which supports the barrier and improves tone at the same time. The order is what matters. Repair first, then stimulate.
Before You Add Anything, Stop These
Almost everyone in this position is trying to solve it by adding. Another active, another supplement, another elimination, another appointment. I understand the impulse completely, and it is usually the wrong direction. Subtraction is a legitimate intervention; it works faster than most people expect, and it costs nothing.
So before you change a single thing about what you are taking, stop these.
- Stop exfoliating more than once or twice a week, and stop entirely for two weeks if your skin currently stings. Stop layering actives. If you are using five products with an active ingredient, you are almost certainly working against yourself. Stop using foaming cleansers that leave your face feeling squeaky, because that sensation is stripped, not clean. Stop the alcohol-heavy toners.
- Stop removing foods. I know that one is hard, because eliminating something feels like doing something. If your reaction list has been growing, that is information about your barrier, not about the food.
- Stop picking and stop the extended mirror inspections, which I say knowing exactly how hard it is. Both worsen inflammation, both extend healing, and both raise cortisol, which is already part of the picture.
And if someone is about to prescribe you another round of antibiotics for your skin, it is worth asking what the plan is afterward, because the round you take this month is the microbiome you will be working with next year.
Give that two weeks before you add anything. A meaningful number of people see their skin calm down on subtraction alone, and even when it does not, you have removed the noise and can finally tell what is actually helping.
The Order of Operations
If you take one thing from this article, let it be this: sequence matters more than any individual intervention you choose. Heal, then restore, then optimize.
You start by opening the exits. Drainage, bile flow, regular bowel movements, liver support, nervous system regulation, and stable blood sugar all come first, because you do not want to mobilize anything before it has somewhere to go. Skipping this step is the single most common reason people feel worse on a protocol that should have helped them, and it is why so many give up in week three convinced that something is uniquely wrong with them.
Only then do you address overgrowths, whether bacterial, fungal, or something else, depending on what is genuinely there rather than what seems likely. This is the stage where testing earns its cost, because guessing here is slow and expensive, often taking months rather than weeks.
After that come repairing the lining, restoring the microbiome, rebuilding the barrier, feeding diversity, and reestablishing the tolerance that got lost somewhere along the way. Then foods come back methodically, not all at once and not never, which are the two mistakes people alternate between. And finally you rebuild for resilience with maintenance nutrition that fits your actual life, continued support where it is needed, and attention to long-term hormonal balance.
Most people, understandably, start at the second or third step, on a system that was never prepared for it. That is the whole difference between a protocol that holds and one that relapses six weeks after it ended.
What Testing Actually Looks Like
I have said twice now that testing earns its cost at a particular stage, so it is only fair to tell you what that means rather than leaving it as a mystery you have to book a call to solve.
For the gut, a comprehensive stool analysis is the workhorse. It shows you bacterial balance, opportunistic overgrowth, yeast, inflammatory markers like calprotectin, digestive markers like elastase, and secretory IgA, which tells you something about immune function at the gut lining. If small intestinal bacterial overgrowth is on the table, that is a separate breath test rather than something stool testing answers, which is a distinction worth knowing before you pay for the wrong one.
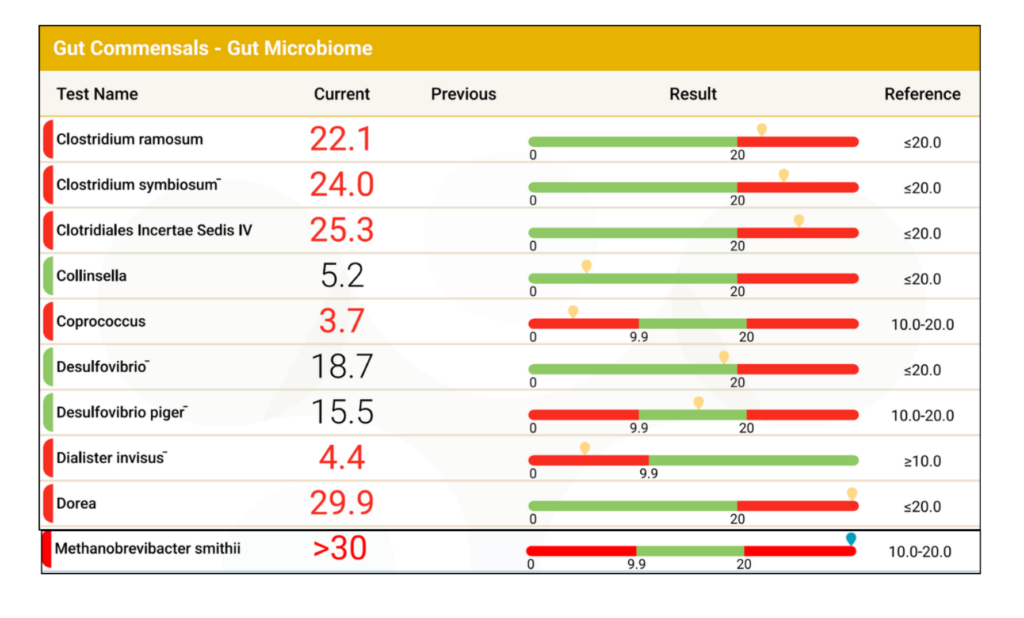
For inflammation and nutrients, an organic acids test gives you a picture of mitochondrial function, detox capacity, and microbial byproducts, and a fatty acid panel tells you where your omega balance actually sits rather than where you assume it does.

For hormones, a comprehensive panel run at the right point in your cycle, ideally one that shows how you are metabolizing estrogen rather than only how much you have. A DUTCH test is great for assessing how you metabolize your hormones and better identifying root causes.

You can read more about the testing we do at Rachel Scheer Nutrition HERE and even download sample lab reports.
What to Expect, Honestly
You have been promised quick results before, and it did not hold, so I would rather tell you the unglamorous version.
Your skin replaces itself about every 28 days, which sets a floor for how quickly visible change can happen, no matter what you do. One cycle is the earliest you should expect to see anything real. For something chronic that has been running for years, three to six months is the honest range, and the deeper work tends to show up later in that window rather than at the start.
It is also not linear, and I want you to know that in advance so it does not derail you. Some people have a stretch in the first few weeks where things look worse before they look better, particularly when overgrowths are being addressed, or detox pathways are opening up. There is often a premenstrual flare in month two that feels like proof it is not working. It usually is not. The pattern that tells you something is genuinely shifting is that the flares get shorter, the lesions heal faster, and the marks fade sooner, and those changes show up before overall clarity does. Watch those three things rather than the count of what is on your face today.
Week three is where most people quit, and now you know it is coming.
I am not going to promise you an outcome. You have been promised things before, and part of why you are here is that they did not hold. What I can tell you is that when the actual driver is addressed in the right order, skin that has not responded to anything for years frequently responds, and I have watched it happen enough times to say it plainly.
What You Can Do This Week
None of what follows requires testing, a practitioner, or a single supplement, and all of it will do more for your skin than another serum.
Anchor every meal in protein, because collagen, keratin, and every repair enzyme you have are built from amino acids, and most of the women I work with are eating roughly half of what they need. Aim for twenty-five to thirty-five grams of fiber a day from as wide a range of plants as you can manage, since variety matters more than volume here: plant diversity is what drives bacterial diversity, which is what drives butyrate. Eat fatty fish a couple of times a week and stop discarding your egg yolks, because the fats that build your cell membranes are not optional and most people are running low on them.
Eat your carbohydrates alongside protein, fat, and fiber rather than on their own. Space your meals three or four hours apart instead of grazing, which supports both blood sugar and the migrating motor complex, the wave that sweeps your small intestine clean between meals and only runs when you are not eating. Take two minutes before you eat to slow your breathing and make your exhale longer than your inhale, because digestion is a parasympathetic function and it simply does not function properly in a braced body. And wear broad-spectrum sunscreen every day.
That is the foundation, and it is the same for everyone because these things support every one of the systems we have talked about. What comes next is not the same for everyone, which is the whole point of the article.
So add one thing on top of the foundation, chosen based on the pattern you recognized earlier. If it is androgen and blood sugar, the single highest-return change is protein at breakfast within an hour of waking. If it is fungal, switch your moisturizer to one without the esters that feed yeast. If it is immune and vascular, it is identifying and reducing your two most reliable flush triggers. If it is a compromised barrier, it is the two weeks of subtraction. If it is the nervous system, it is protecting a consistent sleep window and getting outside before you get on your phone.
One foundation, one targeted addition. That is genuinely enough to start with, and it is far more likely to hold than overhauling everything on a Sunday night.
As for supplements, since you are almost certainly wondering: they help, and they are not where I would have you start. The right supplement in the wrong phase does very little, and some of them actively make things worse if drainage is not open first. Food, sleep, blood sugar, and subtraction come first because they change the terrain that everything else acts on. When supplementation does come in, it should be chosen for your specific pattern and phase rather than assembled from what worked for someone else.
It is not glamorous advice. It is the advice that works.
If You Are Doing This on Your Own
Not everyone is going to work with a practitioner, and I would rather you make real progress alone than stall waiting for a version of this you cannot access right now.
Almost everything in the first phase you can do yourself. Blood sugar stability, protein, fiber diversity, membrane fats, meal spacing, sleep timing, nervous system regulation, and the two weeks of subtraction are all free, and together they resolve a meaningful share of cases outright. Nobody needs to supervise you while you eat breakfast.
Where it gets genuinely harder alone is the overgrowth stage, because that is where guessing is expensive. Antimicrobials aimed at the wrong target, or taken before drainage is open, are how people end up feeling worse and concluding the whole approach failed them. If you get through the foundation phase and things have improved but not resolved, that is usually the point where testing and support earn their cost.
If money is the constraint, do the foundation properly for eight weeks first. You will either be substantially better, in which case you have saved yourself a great deal, or you will have a much clearer picture of what remains, which makes any later testing far more targeted and cheaper.
Frequently Asked Questions
Can gut health really cause acne? Gut dysfunction is rarely the sole trigger, but it drives several mechanisms that contribute to acne: systemic inflammation from a permeable intestinal barrier, hormone recirculation via the microbiome, impaired absorption of the nutrients the skin depends on for repair, and a gradual loss of immune tolerance. For many people with chronic acne, it is the most significant contributing factor.
How long does it take for skin to improve after healing the gut? Skin turns over roughly every 28 days, so visible change usually takes at least 1 or 2 cycles. Chronic cases more often run for three to six months, and the deeper work, such as detoxification and microbiome restoration, tends to come later in that window rather than at the beginning.
Why did antibiotics make my skin worse? Antibiotics reduce microbial diversity in both your gut and on your skin, and recovery is often incomplete. Protective bacterial diversity drops and the risk of fungal overgrowth rises, because the organisms that had been keeping yeast in check are gone. Skin that improves on antibiotics and then worsens afterward is a very common pattern.
Can I have a gut issue with no digestive symptoms? Yes. Absorption, barrier integrity, and microbial balance can all be significantly impaired in someone who never experiences bloating. Skin is sometimes the only outward signal you get.
Is my acne hormonal or gut related? Usually both, and they are more connected than they appear. Your gut microbiome directly influences how estrogen is cleared or recirculated, and blood sugar sits upstream of androgen activity at the follicle. Which one to address first depends on your particular pattern.
I came off birth control, and my skin exploded. Will it settle? Usually, yes, though not as quickly as anyone would like. Androgen rebound after stopping hormonal contraception typically builds over the first three to six months and can take a year or more to settle fully. It tends to resolve faster when the underlying drivers get support rather than being left alone, particularly blood sugar stability, nutrient repletion, and gut function, since the pill is associated with depletion of several nutrients your skin depends on.
I did Accutane, and it came back. Does that mean nothing will work? No. Relapse after isotretinoin is common, and it makes sense when you consider that the drug acts powerfully on the sebaceous gland without addressing why the gland was being driven that way. If the underlying hormonal, metabolic, and gut picture remains unchanged, the signal persists even after the drug wears off. That is a reason to look upstream, not a reason to conclude your skin is untreatable.
Should I still be avoiding dairy and gluten? If a food reliably and obviously flares you, respect that for now. But if you are avoiding things because someone told you to, or because you read it somewhere, the more useful question is why your tolerance narrowed in the first place. The aim is to broaden your diet once the barrier is repaired, not to keep subtracting. A shrinking list of safe foods is a signal to look upstream, not a reason to remove one more.
What supplements should I take for my skin? Fewer than you would expect, and later than you would expect. Supplements support a process; they do not replace identifying what is actually driving your symptoms, and the right one taken in the wrong phase does very little. Food, blood sugar, sleep, and stress shape the terrain on which everything else acts, so they come first. When supplementation does come in, it should match your specific pattern and phase.
Does it get worse before it gets better? Sometimes, particularly in the first few weeks, especially when overgrowths are being addressed or detox pathways are opening. It is usually temporary. The signals worth watching are whether flares are getting shorter, lesions are healing faster, and marks are fading sooner, because those improve before overall clarity does.
My hormone labs came back normal. Does that rule out hormonal acne? No. Bloodwork measures circulating hormones. It does not measure how sensitive your skin’s receptors are, or how much hormone is being converted and activated locally within the tissue. Normal labs and a clearly androgen-driven presentation are entirely compatible.
Watch the Full Masterclass
I taught a full session walking through all of this in far more depth than an article allows, covering the root causes behind hormonal, fungal, and bacterial acne, along with rosacea, dermatitis, eczema, and psoriasis, real client cases with the testing that finally explained them, and the exact order I work through with clients.
Find Out What Is Actually Driving Your Skin
One last thing, and then I will let you go.
If you have ever felt shallow for how much this occupies you, I would like to put that down for you. It is on your face. It is the first thing every person you meet sees, and you have canceled plans over it, and you have done the arithmetic in your head about lighting, camera angles, and whether you can get through a work event. That is not vanity. A visible condition carries a real cost, and noticing that cost is not a character flaw.
You have been carrying this a long time, and doing it with more diligence than most people would manage. What has been missing is not effort. It is direction.
Understanding the gut-skin connection tells you where to look, which is genuinely most of the battle. What it does not tell you is what to address first, what testing is worth paying for, or how to sequence the work so the results you get actually hold.
That is what the assessment is for. Ten questions and about four minutes, and you will come out of it with your root cause drivers ranked by how strongly your own symptoms point to each one, along with the eight foundations of clear skin in the order they genuinely need to be addressed.
Take the Root Cause Skin Assessment
Rachel Scheer is a Board Certified Functional Nutrition Practitioner with a BS in Nutrition and Dietetics, and founder of the RSN Institute of Functional Nutrition.
This article is educational and does not diagnose, treat, cure, or prevent any condition. It is not a substitute for evaluation by a physician or dermatologist. Client cases are individual and results vary. Always consult your healthcare provider before beginning any new protocol or supplement.

Rachel Scheer is a board-certified functional nutrition practitioner with a BS in Nutrition Science and Dietetics from Baylor University and the founder of Rachel Scheer Nutrition. After healing her own severe gut dysfunction, she built a practice that has helped thousands of clients address the root cause of chronic illness.
Read This Next
If you’re wondering why SIBO keeps coming back even after antibiotics, antimicrobials, or a restrictive…
The gut skin connection plays a major role in acne, inflammation, hormone balance, digestion, and…
If you’re bloated most days — flat in the morning, distended by evening, “looking pregnant”…



