
Why Your SIBO Keeps Coming Back (And What Conventional Treatment Gets Wrong)

If you’re wondering why SIBO keeps coming back even after antibiotics, antimicrobials, or a restrictive diet, the answer usually goes deeper than the bacterial overgrowth itself. You have done the elimination diet. You took rifaximin, herbal antimicrobials, or both. Your breath test came back negative, and for about six weeks you felt like yourself again.
Then the bloating came back.
If you are reading this while wondering why your stomach looks six months pregnant by 3pm even though you did everything your practitioner told you to do, I want you to hear this clearly. You are not failing your protocol. Your protocol is failing you because it was built to kill bacteria instead of answering the only question that actually matters.
Why did the bacteria get there in the first place?
I spent years on the other side of this. Severe gut dysfunction, a stack of failed diagnoses, thousands of dollars in testing, and a doctor who told me the answer was to remove my large intestine. I healed by 26, and not because someone finally found the right antimicrobial. I healed because I stopped chasing the overgrowth and started treating the reason my body could not keep it out.
That is what this article is about.
Not sure if SIBO is actually what’s going on? Take our free SIBO Symptom and Root Cause Assessment. It takes about 3 minutes and shows you your likelihood of SIBO, plus the specific root-cause categories your answers point to. Take the quiz here.
What SIBO Actually Is
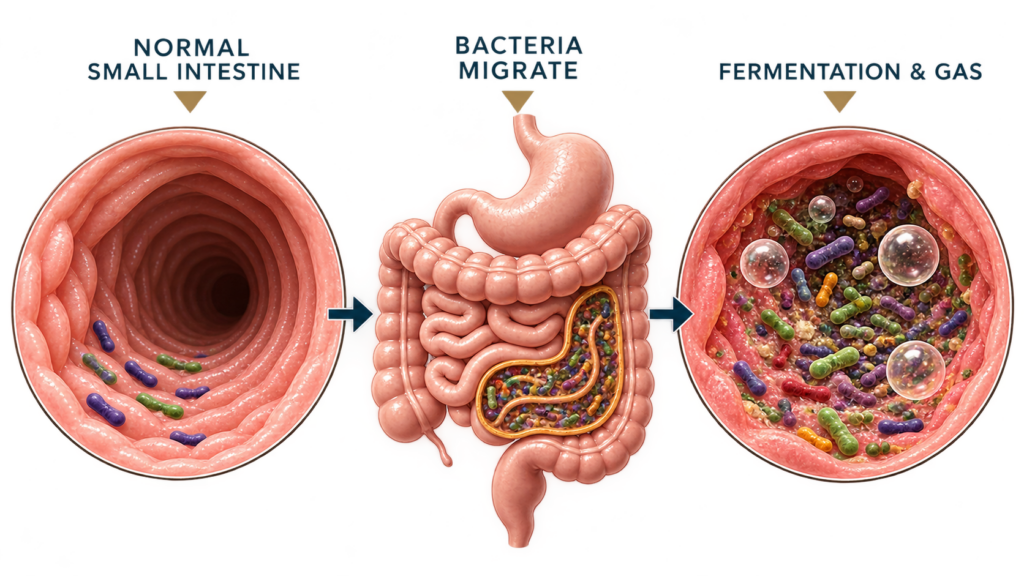
SIBO stands for small intestinal bacterial overgrowth. It is exactly what it sounds like. An abnormal number of bacteria living in the small intestine.
Here is the part most people miss. These are usually not exotic or dangerous bacteria. They are normal bacteria that belong in your large intestine and have migrated up into a place they were never meant to colonize. Location is the problem, not the organism.
When those bacteria sit in your small intestine, they ferment the starches and fibers you eat before your body can absorb them. That fermentation produces gas, and the gas is where the misery starts.
Why It Causes So Much Damage
The overgrowth does not just make you bloated. It creates a cascade.
- The bacteria interfere with normal digestion and absorption, and damage the intestinal lining. This is where leaky gut enters the picture.
- They eat your food before you do. Over time that leads to deficiencies in their favorite nutrients like iron and B12, which shows up as anemia or chronically low ferritin.
- They deconjugate bile, which impairs fat absorption. That means low vitamin A and D, and greasy stools.
- Through the damaged lining, larger undigested food particles pass into the bloodstream where your immune system reacts to them. That is how new food sensitivities appear out of nowhere.
- The bacteria themselves and their cell wall fragments can cross that barrier too. The immune reaction to endotoxin drives chronic fatigue, body pain, and liver burden.
- The acids they excrete can, in high enough amounts, drive neurological and cognitive symptoms.
That is why SIBO never stays a gut problem. It becomes a whole-body problem.
SIBO Symptoms: What to Look For
Most people come to us with some combination of the following:
- Bloating and abdominal gas, usually worse as the day goes on
- Flatulence and belching
- Abdominal pain, cramping, or general discomfort
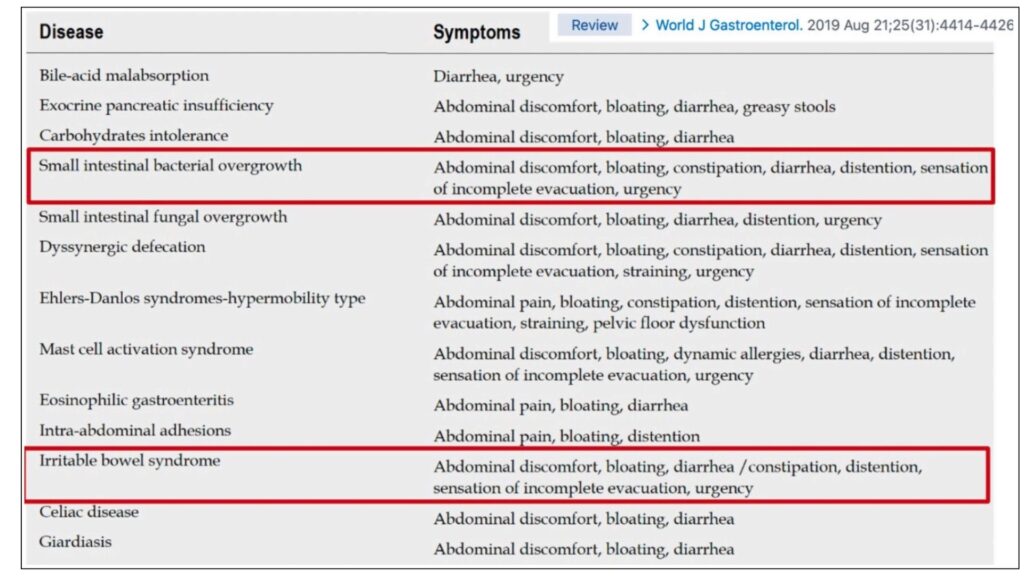
- Constipation, diarrhea, or alternating between the two
- Heartburn and reflux
- Nausea
- Malabsorption signs like fatty stools, anemia, or low ferritin
- Systemic symptoms including headaches, joint and muscle pain, fatigue, brain fog, and rosacea
That last category is the one conventional care almost always misses. When your skin is breaking out, and your joints ache, and you cannot think clearly, nobody connects it back to your small intestine.
The IBS and SIBO Connection
If you have been handed an IBS diagnosis, pay attention here.
IBS is not a diagnosis. It is a description of your symptoms with a Latin coat of paint. It tells you that your bowel is irritable. It does not tell you why.
Research has found that a significant portion of people diagnosed with IBS test positive for SIBO, with some studies putting that number as high as 78 percent. Estimates vary widely depending on the testing method used, but the direction is consistent. A large share of IBS is undiagnosed bacterial overgrowth.
Which means if you were told you have IBS and sent home with a fiber supplement and a suggestion to manage your stress, you may have never been evaluated for the thing actually causing your symptoms.
Here Is the Part Nobody Tells You: SIBO Is a Symptom, Not a Root Cause
This is the single most important idea in this article.
SIBO has a relapse rate of roughly 45 percent. Nearly half of people who successfully clear overgrowth will have it return.
That statistic should stop the entire conversation. If a treatment works and half of patients relapse, the treatment is not addressing the actual problem.
Your small intestine has defenses that are supposed to keep bacteria out. Two in particular.
Your digestive secretions. Stomach acid, pancreatic enzymes, and bile are antibacterial. They sterilize your food as it moves through. When these run low, bacteria survive the journey.
Your migrating motor complex. The MMC is a cleansing wave that sweeps through your small intestine roughly every 90 minutes between meals. It is generated by your enteric nervous system and the hormone motilin, and its job is to push bacteria and debris downstream into the large intestine where they belong. In SIBO, this wave is almost always impaired, allowing bacteria to sit and multiply.
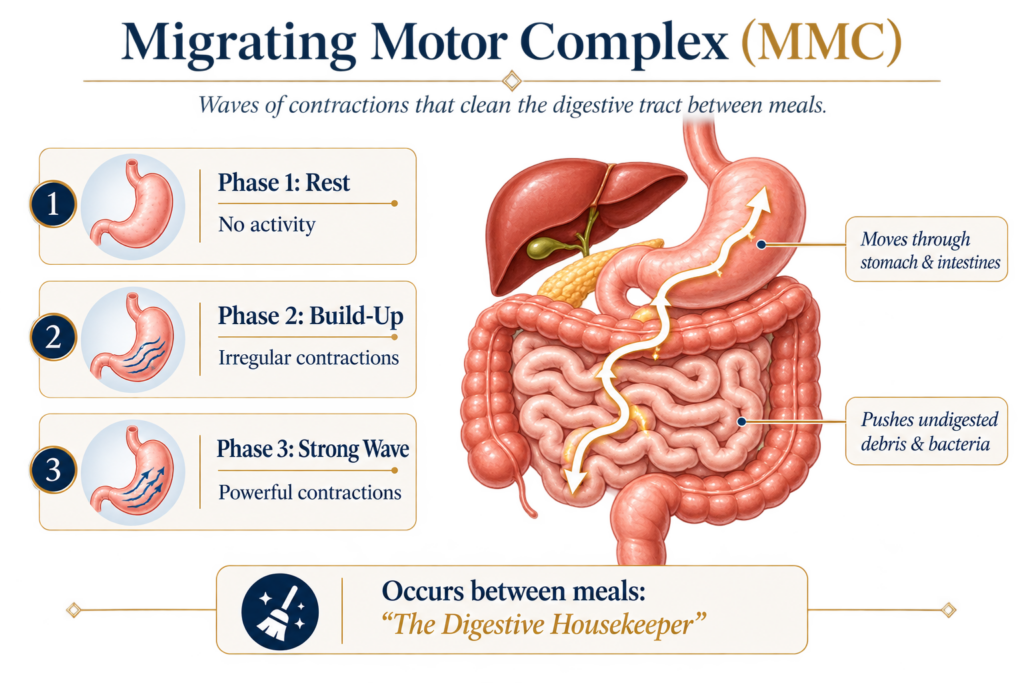
Bacteria do not overgrow in a small intestine that is working properly. They overgrow when the defenses fail.
So when you kill the bacteria without repairing the defenses, you have not solved anything. You have cleared the field for the exact same thing to happen again.
Why Most SIBO Treatments Fail

SIBO has a relapse rate of 45%
In my practice, failed SIBO cases almost always fall into the same five patterns.
1. Only focusing on eradication. The entire plan is antimicrobials. Kill, retest, done. Nothing about why it happened.
2. Not healing the gut afterward. The overgrowth damaged your intestinal lining. If you clear the bacteria and never repair that lining, you are left with leaky gut, food sensitivities, and malabsorption that keep the cycle going.
3. Not addressing the underlying root cause. Nobody asked about your car accident, your food poisoning in Mexico, your C-section, your thyroid, or the fact that you have been in fight-or-flight for a decade.
4. No prevention or maintenance plan. No prokinetic support, no digestive support, no meal spacing strategy. You are discharged with nothing holding the door shut.
5. Not looking beyond SIBO. Sometimes SIBO is real and treated, and you still have symptoms, because there is something else going on underneath it.
Want the full clinical breakdown? I walk through all of this, plus real client cases and the exact protocols we run, in our free Beyond SIBO Masterclass. Take our SIBO root-cause quiz, then access the training.

The 4 Categories of SIBO Root Causes
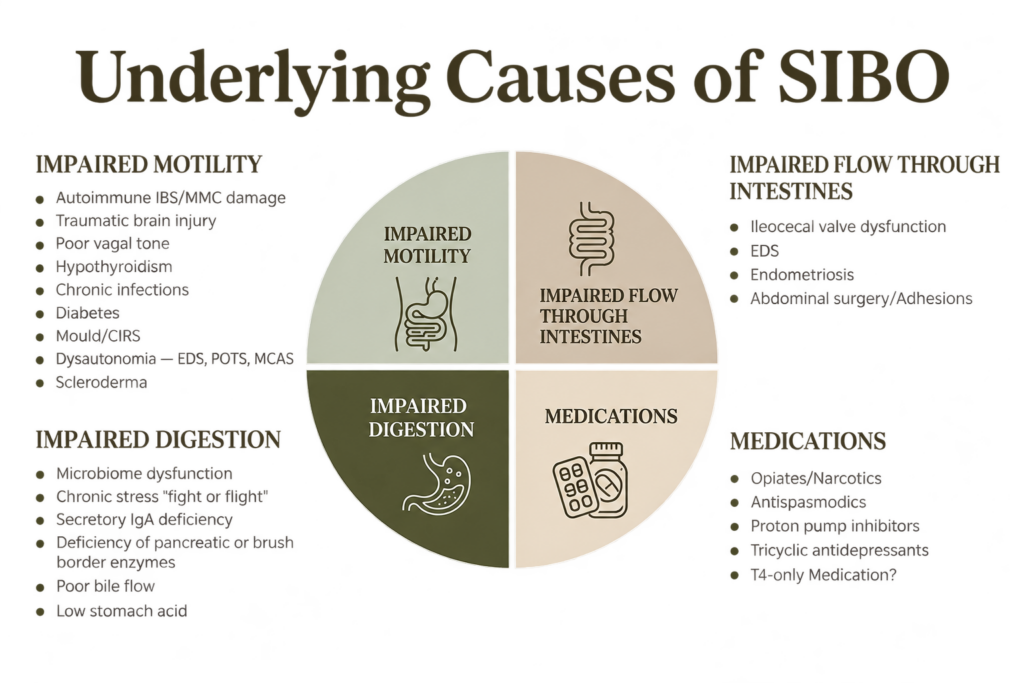
When we evaluate a new client, we look at which of the four categories broke down. Most people have more than one.
1. Impaired Motility
Anything that damages or slows the migrating motor complex.
- Post-infectious autoimmunity. A case of food poisoning or traveler’s diarrhea lasting more than 24 hours can trigger an autoimmune response against the nerve cells that run your MMC. This is one of the most common causes we see, and it can be traced back for years.
- Traumatic brain injury. Concussions, whiplash, car accidents, sporting injuries, or a hard fall on the tailbone. Head and spine trauma disrupts the vagal signaling that drives gut motility.
Poor vagal tone and chronic sympathetic dominance. You cannot run the MMC from fight-or-flight. - Hypothyroidism. Low thyroid slows everything, including transit time.
- Diabetes and metabolic syndrome. Elevated blood sugar damages the nerves that control motility.
Chronic infections, mold, and CIRS. - Dysautonomia, including EDS, POTS, and MCAS.
- Scleroderma and other connective tissue diseases.
2. Impaired Digestion
When stomach acid, enzymes, or bile are low, food enters the small intestine undigested and becomes bacterial fuel.
- Low stomach acid, including from autoimmune gastritis
- H. pylori infection
- Pancreatic insufficiency or brush border enzyme deficiency
- Poor bile flow
- Secretory IgA deficiency
- Chronic stress, which shuts down digestive secretion at the source
3. Structural Abnormalities and Adhesions
This is the most underdiagnosed category by a wide margin.
Scar tissue forms extremely easily inside the abdomen. Think of it as a kink in a garden hose. The bacteria physically cannot be swept out, no matter how good your motility is elsewhere.
Consider adhesions if you have had any of the following:
- Laparoscopy or laparotomy
- C-section
- Hysterectomy
- Appendectomy
- Gallbladder removal
- Hernia repair or bowel obstruction repair
- Back or hip surgery, or gastric bypass
- Endometriosis, pelvic inflammatory disease, or ruptured ovarian cysts
Ileocecal valve dysfunction and connective tissue disorders like EDS belong here too.
4. Medications
Several extremely common prescriptions directly suppress motility or digestion.
Opiates and narcotics. Hydrocodone, morphine, oxycodone, hydromorphone, fentanyl.
Antispasmodics. Anticholinergics such as dicyclomine and atropine, and smooth muscle relaxants such as mebeverine.
Proton pump inhibitors. Omeprazole, Nexium, and similar. These reduce the stomach acid that is supposed to sterilize your food.
Tricyclic antidepressants. Amitriptyline, imipramine.
T4-only thyroid medication in people who are not converting well.
The irony is not lost on me. Several of these are prescribed for the very symptoms SIBO causes.
Which categories apply to you? Our SIBO Symptom and Root Cause Assessment maps your history against all four. Take the assessment.
How SIBO Should Actually Be Tested
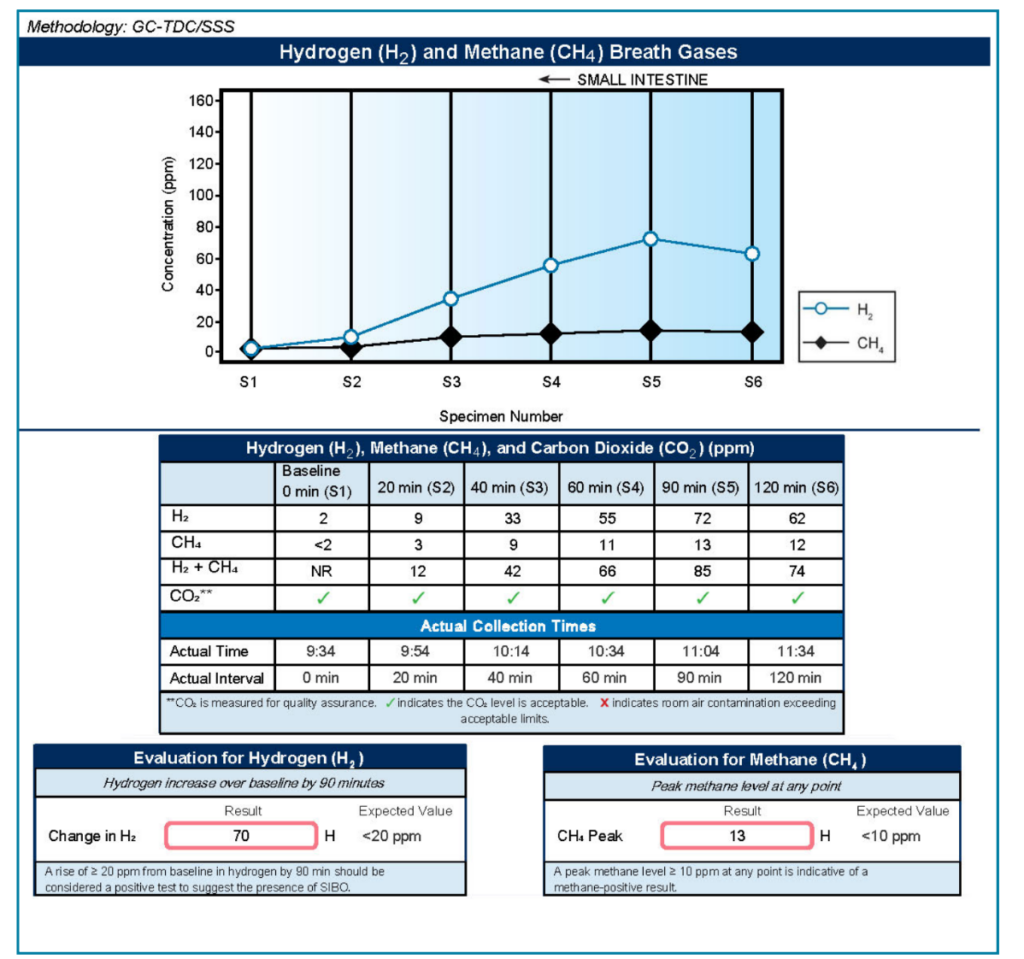
SIBO breath test measuring hydrogen and methane levels
Breath testing is the gold standard
A lactulose or glucose breath test measures hydrogen and methane gas production over a timed series of samples. It is the only definitive diagnostic tool for confirming SIBO.
The gas pattern matters as much as the positive result. Hydrogen-dominant, methane-dominant, and hydrogen sulfide presentations behave differently and require different treatment approaches. A protocol built for the wrong gas type is one of the quieter reasons treatment fails.
Stool testing is complementary, not diagnostic
A comprehensive stool test cannot diagnose SIBO. It can tell you an enormous amount about why you got it, which is arguably more valuable. We use it to assess:
-
- Pathogenic bacteria and parasites contributing to dysbiosis
- Digestive enzyme sufficiency
- Inflammation markers
- Overall microbiome composition
- Intestinal permeability indicators
Root cause investigation is the step everyone skips
A positive breath test tells you what. It does not tell you why. This is where we run full thyroid panels, blood sugar and metabolic markers, hormones, adrenal and stress markers, mycotoxins, heavy metals, and oxidative stress profiles, alongside a detailed history covering surgeries, infections, injuries, and nervous system state.
You cannot prevent a relapse you never understood.
The Gut-Brain Connection Nobody Treats
Your gut and brain talk constantly through four channels: the vagus nerve, hormones, immune signaling, and microbial compounds. Your enteric nervous system holds more than 500 million neurons.
Here is the practical consequence. Your migrating motor complex, your stomach acid, your enzyme output, and your bile flow are all downstream of your autonomic nervous system. When you live in a sympathetic, fight-or-flight state, your body is not prioritizing digestion. It has decided you are being chased.
You cannot heal the body living in a sympathetic state. I say this to nearly every client.
This is why our protocols include nervous system work as a clinical intervention, not a wellness extra. Diaphragmatic breathing, cold exposure, humming, gargling, vocal work, meditation, gentle movement, social connection, and, for severely dysregulated cases, medical interventions like stellate ganglion blocks and vagus nerve resets can be great.
The RSN Approach to SIBO
Our process is built around the sequence that prevents relapse.
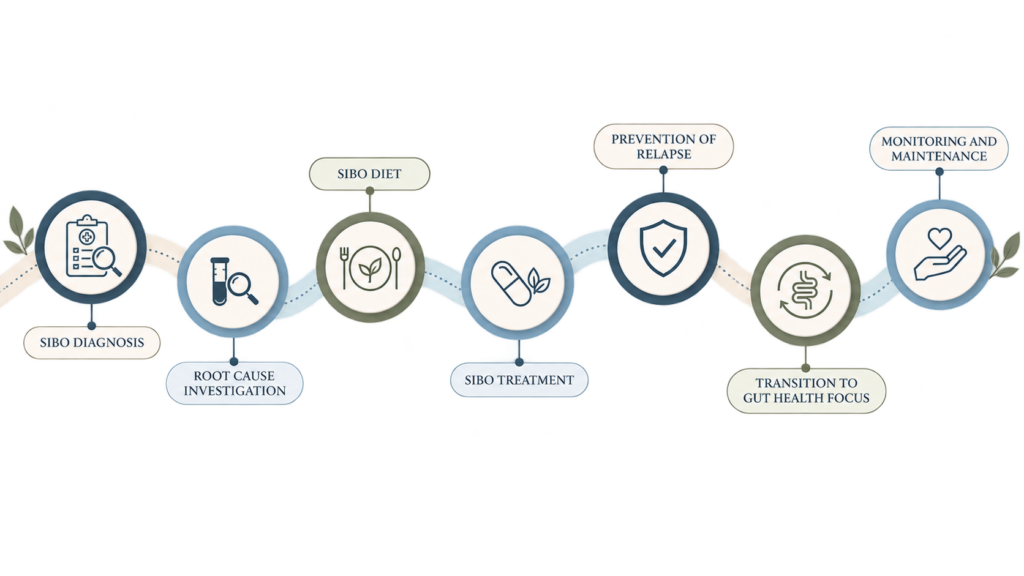
Step 1. Comprehensive intake and advanced testing. Full medical history, symptoms, nutrition, lifestyle, medications, and mental health assessment, paired with advanced labs covering blood chemistry, thyroid, hormones, gut microbiome, heavy metals, mycotoxins, and oxidative stress.
Step 2. Root cause analysis and a custom roadmap. Our practitioners connect your symptoms to your lab results and build a personalized six-month plan. Not a template.
Step 3. The six-month healing intensive. Monthly coaching with root cause protocols, a custom nutrition plan built to your labs, polyvagal-informed coaching to shift you out of fight or flight, and medical oversight when a case is complex.
A typical arc looks like a strategic diet approach and gut repair in the first month, herbal antimicrobials with biofilm disruption in months two and three, structured food reintroduction and lab reassessment in month four, and microbiome diversification plus any needed detox work in months five and six.
Step 4. Retesting and progress validation. Follow-up labs confirm what changed. We do not guess; we verify.
Step 5. Continued care. After the intensive, you keep access to lab testing at cost, supplement discounts, direct provider messaging, and quarterly check-ins. The goal is that you never start over.
What This Looks Like in Practice

Deanna came to us after multiple SIBO treatments with both conventional and functional practitioners. She was an athlete and highly health-conscious, and still nothing held. Her root cause analysis showed low bile and stomach acid, suboptimal thyroid, sympathetic dominance, MMC disruption, oral contraceptive effects, and heavy metal burden. Once we addressed the digestive insufficiency and the nervous system alongside the antimicrobials, it finally stuck.

Martha had already done both elemental and antibiotic protocols. Her workup revealed mycotoxins and heavy metals, poor bile flow, impaired liver detoxification, methylation issues, and eventually confirmed adhesions. She needed visceral manipulation and later surgical release. No antimicrobial on earth was going to fix a mechanical obstruction. Her bloating dropped significantly, her skin reactions nearly resolved, and her energy came back.
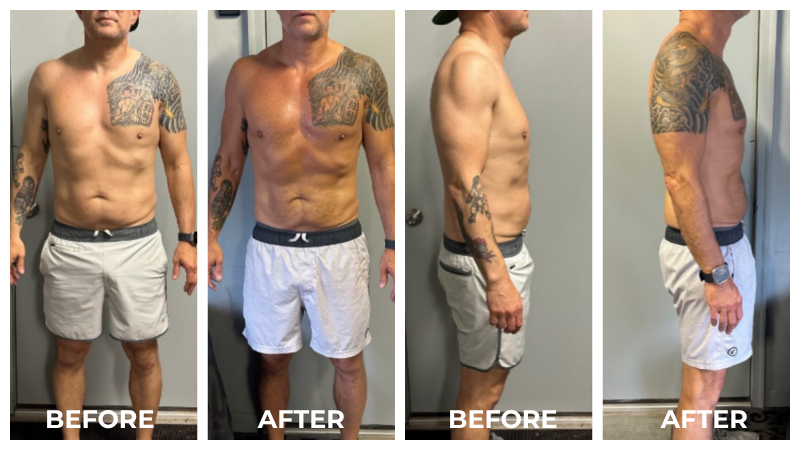
Daniel was a founder and CEO with anxiety, loose stools, bloating, and recurrent diverticulitis flares. Underneath: dysbiosis with SIBO, parasites, sympathetic dominance, years of antibiotics, leaky gut, insulin resistance, and elevated inflammatory markers. He needed a parasite protocol and somatic breathwork as much as he needed a gut protocol.
Three people, all diagnosed with SIBO. Three completely different reasons it happened.
Beyond SIBO: When It Is Not SIBO At All
Sometimes we test, and SIBO is not the answer, or it is only part of it. Other drivers of IBS-type symptoms include food sensitivities and histamine intolerance, bile acid malabsorption, broader gut dysbiosis, intestinal hyperpermeability, HPA axis dysfunction, mast cell activation, primary motility disorders, pancreatic insufficiency, low stomach acid, parasites and candida overgrowth, heavy metal toxicity, hormonal imbalances tied to your cycle, vagus nerve dysfunction, and environmental toxin exposure.
This is exactly why we test instead of assume.
Frequently Asked Questions
How do I know if I have SIBO? The only way to confirm it is with a lactulose or glucose breath test that measures hydrogen and methane. That said, a symptom and history assessment can tell you how likely it is and which root causes to investigate before you spend money on testing.
Why does SIBO keep coming back after antibiotics? Because antibiotics remove the bacteria without repairing what let them accumulate. If your motility, digestive secretions, or intestinal structure are still compromised, the overgrowth will return. Relapse rates sit around 45 percent for this reason.
Can SIBO be cured permanently? It can be resolved and kept resolved, but only by treating the underlying cause rather than the overgrowth alone. Someone with autoimmune MMC damage may need ongoing prokinetic support. That is management of a root cause, which is very different from repeatedly killing bacteria.
Is a low FODMAP diet enough to fix SIBO? No. Dietary approaches like low-FODMAP, SCD, or a bi-phasic diet reduce symptoms by starving the bacteria, making them useful during treatment. They do not eradicate overgrowth or address the underlying cause, and staying on them long-term can reduce microbial diversity.
How long does it take to heal SIBO? For a straightforward case with one clear root cause, a few months. For cases involving adhesions, mold, heavy metals, or significant nervous system dysregulation, a duration of 6 months or more is realistic. Our program is built as a six-month intensive because that is what the process actually requires.
Can stress cause SIBO? Yes, and it is one of the most overlooked drivers. Chronic sympathetic activation suppresses gastric acid secretion, enzyme output, and bile flow, and impairs the migrating motor complex. Stress is not the whole story, but it is very often part of it.
Your Next Step
If you have been cycling through protocols and getting temporary relief, the answer is not another round of antimicrobials. It is finding out what is driving it.
Start with the free SIBO Symptom and Root Cause Assessment. It takes about three minutes. You will get your likelihood of SIBO based on your symptom pattern and the specific root-cause categories your history points to.
Right after you finish, you will get access to our Beyond SIBO Masterclass, where I walk through the full clinical framework, real client cases, and exactly how we build protocols that hold.
And if you want to stop researching and start fixing this with a team, book a call with Rachel Scheer Nutrition to talk through your case.
You are not broken. Your body has been asking for something specific for a long time. Let’s find out what it is.
Rachel Scheer is a board-certified functional nutrition practitioner with a BS in Nutrition Science and Dietetics from Baylor University and the founder of Rachel Scheer Nutrition. After healing her own severe gut dysfunction, she built a practice that has helped thousands of clients address the root cause of chronic illness.
This article is for educational purposes and is not medical advice. Please consult your medical provider regarding your individual case.

Rachel Scheer is a board-certified functional nutrition practitioner with a BS in Nutrition Science and Dietetics from Baylor University and the founder of Rachel Scheer Nutrition. After healing her own severe gut dysfunction, she built a practice that has helped thousands of clients address the root cause of chronic illness.
Read This Next
If you’re wondering why SIBO keeps coming back even after antibiotics, antimicrobials, or a restrictive…
The gut skin connection plays a major role in acne, inflammation, hormone balance, digestion, and…
If you’re bloated most days — flat in the morning, distended by evening, “looking pregnant”…



